Tel. (+52) 686 405 1012 USA: (+1) 442 231 0496 Mon-Sat: 8:00AM - 7:00 PM


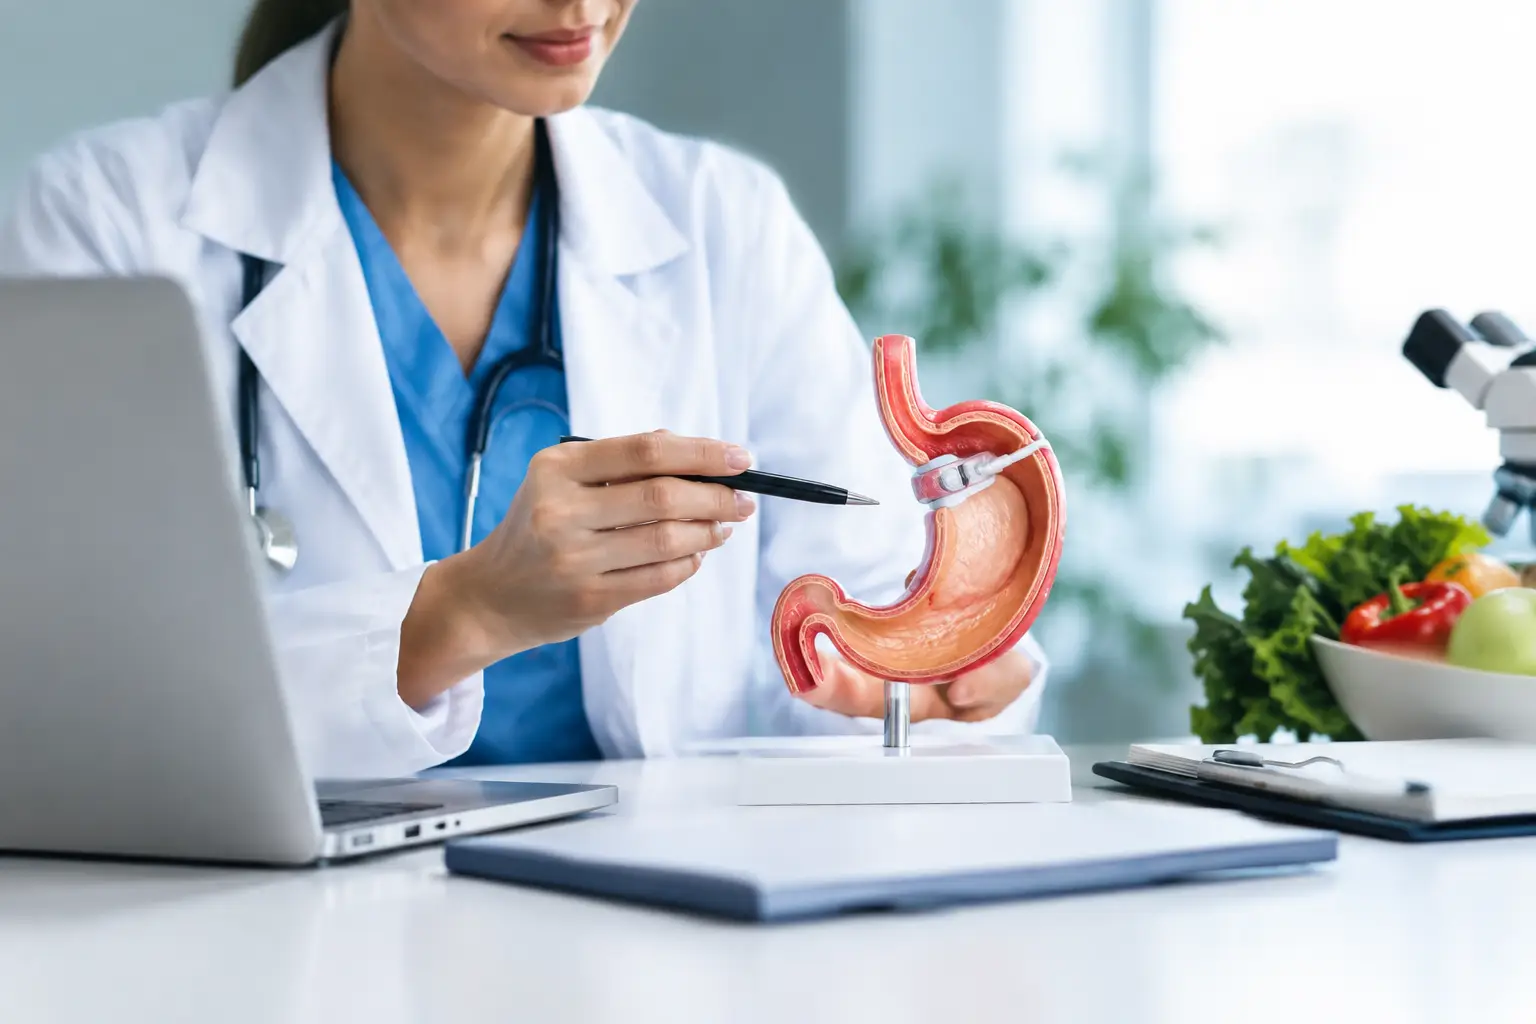
For many people considering bariatric care, the question is no longer simply, “How much weight can I lose?” Current metabolic surgery research trends are focused on a broader outcome: how a procedure may affect blood sugar, blood pressure, fatty liver disease, sleep apnea, mobility, and long-term quality of life. That shift matters because obesity is a complex chronic disease, not a failure of willpower.
Surgery is not the right choice for every person, and research does not replace an individual medical evaluation. Still, the direction of the evidence gives patients a more complete way to compare gastric sleeve, gastric bypass, mini gastric bypass, and less invasive options such as an intragastric balloon.
Metabolic Surgery Research Trends That Matter to Patients
The strongest trend is the move from measuring pounds lost to measuring health improved. Weight loss remains meaningful because it can reduce strain on joints, improve energy, and make daily movement easier. But medical teams are also looking at whether patients need fewer diabetes medications, experience better glucose control, see improvement in liver health, or reduce cardiovascular risk factors.
This is why the term metabolic surgery is increasingly used alongside bariatric surgery. Procedures that change stomach capacity and food flow can affect appetite, satiety, insulin sensitivity, and gut hormones. The exact response varies from patient to patient, but the goal is not cosmetic weight change alone. It is to support healthier metabolic function over time.
Earlier intervention for appropriate candidates
Historically, bariatric surgery was often discussed only when a patient had a very high BMI or severe obesity-related disease. Research and clinical guidelines have increasingly recognized that some patients with a BMI below those older thresholds may still benefit from metabolic treatment, especially when type 2 diabetes or other significant health conditions are difficult to control.
That does not mean every adult with a BMI of 30 should pursue surgery. Eligibility depends on medical history, prior weight-loss efforts, current conditions, medication use, psychological readiness, and the ability to follow lifelong nutrition and follow-up recommendations. The important change is that BMI is no longer the only part of the conversation.
For patients who have spent years cycling through restrictive diets, exercise plans, and medication changes without sustained results, a specialist can help determine whether a structured metabolic intervention is medically reasonable.
Better understanding of diabetes improvement
One of the most closely watched areas of research is type 2 diabetes. Some patients see blood sugar improve rapidly after gastric bypass or sleeve surgery, sometimes before major weight loss occurs. Researchers continue to study the hormonal and metabolic mechanisms behind this response.
Gastric bypass has a long history of strong metabolic effects, particularly for patients with type 2 diabetes. Sleeve gastrectomy can also produce meaningful improvements while preserving a simpler digestive pathway than bypass. Mini gastric bypass may be considered in selected cases, although it requires a careful discussion of reflux, nutritional monitoring, and procedure-specific risks.
No procedure guarantees diabetes remission. Duration of diabetes, pancreatic function, current medications, age, and the amount of weight lost after surgery can all influence outcomes. Even when a patient reduces or stops medication, ongoing laboratory monitoring remains essential. Diabetes can return, particularly if weight is regained or metabolic risk changes over time.
Research Is Looking Beyond the Scale
A lower number on the scale can be encouraging, but it does not tell the entire story. Newer studies increasingly track outcomes that patients feel in everyday life: walking without pain, sleeping better, having more stamina, fitting more comfortably in a seat, or being able to participate in family activities.
Heart, liver, and sleep health
Obesity is associated with several conditions that may improve when substantial, sustained weight loss is achieved. Research continues to examine how metabolic surgery affects high blood pressure, abnormal cholesterol levels, obstructive sleep apnea, and metabolic dysfunction-associated steatotic liver disease, often called fatty liver disease.
Improvement is common for many patients, but the outcome is not automatic. A patient with longstanding hypertension may still need medication after surgery, although the dose or number of medications may change. Sleep apnea may improve significantly, but a repeat sleep study is often needed before stopping CPAP therapy. These details are why coordinated follow-up with primary care and specialty providers is so important.
Long-term weight maintenance, not just early results
The first 12 to 18 months after surgery often receive the most attention because this is when weight loss is usually most visible. Research is placing greater emphasis on what happens five, 10, or more years later.
Long-term success is influenced by the procedure itself, but also by behavior, nutrition, mental health, activity level, follow-up attendance, and treatment of weight regain when it occurs. Weight regain should not be viewed as personal failure. It can be a medical signal that deserves evaluation. Depending on the situation, care may include nutritional support, behavioral counseling, anti-obesity medication, endoscopic treatment, or revisional surgery.
This is one reason patients should choose a program that treats surgery as the beginning of a care relationship, not a single transaction.
Procedure Selection Is Becoming More Personalized
There is no universally “best” bariatric procedure. Research increasingly supports matching the operation to the patient rather than applying the same solution to everyone.
Gastric sleeve surgery is widely used because it is effective, performed laparoscopically, and does not reroute the intestines. It may be a strong option for many patients, but preexisting reflux deserves special attention because reflux can worsen after a sleeve in some cases.
Gastric bypass may be recommended when a patient has significant reflux, type 2 diabetes, or particular weight-loss goals. It can provide powerful metabolic benefits, yet it also requires lifelong attention to vitamin and mineral supplementation because the digestive pathway is changed.
Mini gastric bypass can offer effective weight loss and metabolic improvement for selected patients, but it is not interchangeable with standard bypass. Its potential advantages and concerns, including bile reflux and nutritional risks, should be reviewed with an experienced bariatric surgeon.
A swallowable intragastric balloon may be appropriate for patients seeking a non-surgical, temporary tool to support weight loss and lifestyle change. It is less invasive than surgery, but results are generally more modest and depend heavily on nutrition and activity habits. It may be useful for some patients with lower BMI ranges or those who are not ready for an operation.
Safety Research Favors Prepared, Accredited Care
Modern laparoscopic bariatric surgery has become safer as surgical techniques, anesthesia, preoperative screening, and postoperative protocols have improved. Yet every procedure carries risk. Bleeding, infection, blood clots, leaks, dehydration, nutritional deficiencies, and anesthesia complications must be discussed plainly before treatment.
For patients traveling from the United States to Mexicali, the research question is not only which procedure to choose. It is also how to organize safe care across the border. Patients should understand who performs the operation, what credentials the surgeon holds, where the surgery takes place, what preoperative testing is included, how complications are handled, and what follow-up plan will be available after returning home.
Transparent package details are helpful, but price should never be the only decision factor. A clear plan for surgeon access, medications, nutrition, transportation, lodging when included, and postoperative communication can reduce avoidable stress during recovery.
What to Ask During a Metabolic Surgery Consultation
A productive consultation should feel like a medical discussion, not a sales presentation. Ask how your medical conditions affect procedure choice, what realistic weight-loss range applies to patients with a similar starting profile, and how your current medications may change after surgery.
It is also reasonable to ask about reflux, vitamin requirements, pregnancy planning, alcohol use, mental health support, expected recovery time, and the clinic’s approach if weight loss slows or weight regain occurs. If you are traveling, ask for a step-by-step explanation of arrival, hospital care, discharge, hotel recovery, transportation, and communication after you return home.
The best next step is a personalized evaluation with a qualified bariatric team that can look beyond BMI and help you weigh health goals, risks, travel needs, and the level of long-term support you will need to feel confident in your decision.